
BuddhistCatholicContemplativeEvangelicalGeneral ChristianHinduJewishLatter-day SaintMuslimNew VisionsProgressive Christian
Beliefs
- Buddhist
- Catholic
- Contemplative
- Evangelical
- General Christian
- Hindu
- Jewish
- Latter-day Saint
- More Voices
- Muslim
- New Visions
- Pagan
- Progressive Christian
Topics
- Religion News
- Food and Religion
- Sports and Religion
- Religious Art
- Religious Music and Entertainment
- Religious Events
- History and Religion
- Style and Religion
- Politics and Religion
- Women in Religion
- Recreation Outdoors and Religion
- Business Finance and Religion
- Careers Workplace and Religion
- Education and Religion
- Family Parenting and Religion
- Health Fitness and Religion
- Home and Religion
- Relationships and Religion
- Technology and Religion
- Travel and Religion
Columnists
- Buddhist Columnists
- Business Finance and Religion Columnists
- Careers Workplace and Religion Columnists
- Catholic Columnists
- Contemplative Columnists
- Education and Religion Columnists
- Evangelists Columnists
- Family Parenting and Religion Columnists
- General Christian Columnists
- Health Fitness and Religion Columnists
- Hindu Columnists
- History and Religion Columnists
- Home and Religion Columnists
- Jewish Columnists
- More Voices Columnists
- Latter Day Columnists
- Muslim Columnists
- New Visions Columnists
- Nonreligious Columnists
- Pagan Columnists
- Politics and Religion Columnists
- Progressive Columnists
- Recreation Outdoors and Religion Columnists
- Relationships and Religion Columnists
- Religion News Columnists
- Religious Art Columnists
- Religious Events Columnists
- Religious Music and Entertainment Columnists
- Sports and Religion Columnists
- Style and Religion Columnists
- Technology and Religion Columnists
- Travel and Religion Columnists
- Women in Religion Columnists
Resource Library
- 2026 Calendar
- Library of World Religions
- The 100 Most Holy Places on Earth
- Patheos Answers
- Podcasts
- Videos
- Faith Leaders Database
- Anglican Episcopalian
- Bahai
- Baptist
- Buddhism
- Christianity
- Confucianism
- Eastern Orthodoxy
- Hinduism
- Holiness and Pentecostal
- ISKCON
- Islam
- Judaism
- Lutheran
- Methodist
- The Church of Jesus Christ of Latter-day Saints
- New Age
- Paganism
- Presbytarian and Reformed
- Protestantism
- Religion Behind the Scenes
- Roman Catholic
- Scientology
- Shia Islam
- Sikhism
- Sufism
- Sunni Islam
- Taoism
- Zen
- See all religions
Research Tools
 Ad-Free & Subscriber Log-In Subscription Support
Follow Patheos 

- Trending:
- Forgiveness
- |
- Marriage
- |
- Consciousness
- |
- Death Penalty
- |
- Election
- |
- Halloween
 Thin Places-Faith, Family and Disability
- Home
- Family, Parenting and Religion
- Sam Was a Gift to Us: A father reflects on medical advances, trisomy 18, and human fragility
Sam Was a Gift to Us: A father reflects on medical advances, trisomy 18, and human fragility
Last updated on: October 17, 2013 at 6:42 am by Amy Julia Becker
Sam Was a Gift to Us: A father reflects on medical advances, trisomy 18, and human fragility 2013-10-16T08:08:42-04:00 Amy Julia Becker
Patheos Explore the world's faith through different perspectives on religion and spirituality! Patheos has the views of the prevalent religions and spiritualities of the world.
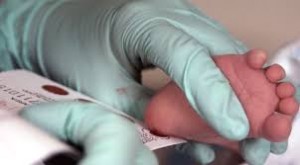
Sam’s footprints
My son, Samuel, died five hours after his birth; he had trisomy 18. The five hours my wife and I spent with him were some of the most significant of our life together. They were a gift to us at the end of difficult pregnancy and a peaceful entry into the long paths of grief.
I mention our story here, at the outset of these reflections, because people with stories like ours are among those who should be most encouraged by the recent discoveries of a potential for chromosome therapy. More than 90% of children with trisomy 18 die within the first year of life (if they are fortunate enough to be born). And the complications associated with trisomy 18 are often extensive. Sam was born with clubbed feet with rocker bottoms, clenched firsts, prominent occiput, and a hole in his heart. The most difficult complication for Sam was a giant omphalocele. During his development, the muscles in Sam’s abdominal wall did not close properly, leaving a large segment of his intestines, his liver, and his spleen enclosed within a thin layer of tissue on the exterior of his abdomen. This omphalocele significantly hindered his pulmonary development, making it difficult for him to breathe on his own. Ultimately, it also brought about his early death. The thought that there might be something we could do to provide a less limiting life for our children provides a flicker of hope.
I have only a small glimpse of what it means to care for a child with a life-limiting condition and a significant part of me wants to celebrate these discoveries. No parent wants his or her child to experience the suffering of disease, disability, or impairment. Provided that these therapies may one day be safe and effective, it is not clear how one would distinguish these from other widely employed forms of medical care. Nonetheless, I am ambivalent about the implications of this research. In the space that remains, I want to offer just a few of my reasons.
First, it is not clear to me who my son Samuel would have been independent of his trisomy 18. It seems to me that this was simply part of who he was as a person. I have no doubt that researchers are seeking therapies that would target the deleterious effects of the condition, but this assumes that treating, or eradicating, the characteristic effects of a trisomy is possible without altering or affecting the nature of the person. It is not clear to me that advocates of these novel approaches have shown that this is the case for the envisioned therapies, particularly if the therapeutic intervention would occur early in embryological development in order to prevent the broad manifestation of the condition.
Second, the language of “curing” raises concerns about (thinly) veiled moral assessments of the value of a person’s life. In our experience, the medical language concerning trisomy 18 was morally loaded. Immediately after receiving Sam’s diagnosis, we were asked whether we wanted to “interrupt” the pregnancy. This failed attempt at euphemism followed a lengthy discussion of the fact that trisomy 18 was a “lethal chromosomal abnormality” and a “fatal anomaly.” To the doctors’ credit, they did not use the term “incompatible with life,” but many in our circumstances have heard this wrenching phrase. This language may deliver realistic expectations about the child’s prognosis, but it also suggests to parents who are trying to cope with devastating news that their child is already dead, or might as well be dead. It is difficult to reconcile this “realism” with the child whose movements give jabbing reminders that he or she is really alive. The language of “curing” seems to commit one to a similar notion that the child with trisomy 18 has a deficient form of life.
Discussion of this sort raises an important question about the meaning of the term “curing.” In this context, should we take it to mean something like “eradicating” or “preventing” trisomy 18? If this is how we are to understand this pursuit, then therapeutic interventions would need to occur early in embryological development. This approach would be the one most likely to halt, silence, or reverse the broad effects to which trisomy 18 can give rise. It is this approach that would prevent the manifestation of the underlying condition.
I think there are substantive concerns one ought to have about this kind of “therapeutic” practice. In particular, one should consider how this might alter the relations between parent and child. As we waited for Sam’s birth, I was constantly reminded of the obstacles we were facing: vulnerabilities that emerged from our humanness and the limited capacities of medicine to solve the problem of our mortality. New advances in biomedical technology predict a new kind of power to overcome these frustrating barriers. But the fact that it might be possible to push back against our finitude does not make this new capacity something worth seizing. Before we employ these powers we should ask whether the medical interventions envisioned to “cure” persons with a trisomy will entrench within us a weakened disposition to welcome our children as gifts to be loved. And we should consider whether these new techniques will heighten the fearful tendencies that push us into desperate and despairing attempts to immunize ourselves and our children from our fragility as humans.
I’ll end here where I began: Sam was a gift to us. He was by nature vulnerable and dependent. But this is true of every human life. And it is the same vulnerability and dependence that is a source of our ability to love and be loved. Sam possessed a remarkable capacity to call forth love from us. I wish that he would not have had to experience such a short and limited life. But I’m not yet convinced that the answer to my unfulfilled hopes lies in these medical advances.
Aaron D. Cobb is the author of Loving Samuel: Suffering, Dependence, and the Calling of Love*, a forthcoming work from Cascade Books.*
Aaron and his family live in Montgomery, Alabama where he is an Assistant Professor of Philosophy at Auburn University at Montgomery.
To read more of Aaron’s reflections on Samuel, follow Aaron’s blog.

Browse Our Archives
Select a Category Articles Books Disability Down Syndrome Faith family Perfectly Human Uncategorized
Select a Month February 2014 January 2014 December 2013 November 2013 October 2013 September 2013 August 2013 July 2013 June 2013 May 2013 April 2013 March 2013 February 2013 January 2013 December 2012 November 2012 October 2012 September 2012 August 2012 July 2012 June 2012 May 2012 April 2012 March 2012 February 2012 January 2012 December 2011 November 2011 October 2011 September 2011 August 2011 July 2011 June 2011 May 2011 April 2011 March 2011 September 2010 July 2010 June 2010 May 2010 April 2010 March 2010 February 2010 January 2010 December 2009 November 2009 October 2009 September 2009 August 2009 July 2009 June 2009 May 2009 April 2009 March 2009 February 2009 January 2009 December 2008 November 2008 October 2008 September 2008 August 2008 July 2008 June 2008
TAKE THE
Religious Wisdom Quiz
Who was Esther's cousin and guardian?
Select your answer to see how you score.
Haman Nehemiah Mordecai Ezra
Related posts from Thin Places-Faith, Family and Disability

Thank you Patheos! (And Continuing the Conversation at...
Thin Places-Faith, Family and Disability
My Questions About the Ethics of Embryo Selection
Thin Places-Faith, Family and Disability

I Don't Love Valentine's Day, and That's Okay
Thin Places-Faith, Family and Disability

7 Thoughts on How to Survive Another Snow...
Thin Places-Faith, Family and Disability
TRENDING AT PATHEOS Family, Parenting and Religion

The Real AI Story Is Adoption Without Trust
Artificial intelligence has crossed a political threshold. It is no longer a...

A new article, written by Jeff Lindsay and Gale L. Pooley,...

Swimfan: Forgotten Aughts Pleasures
This is a recovery effort. In 2002, My Big Fat Greek Wedding...

Top Three Anti-Catholic Lies About Catholicism
This is my initial transcript for the video, "THE 3 WORST...

Pope Leo Celebrates Mass for Nurses & Docs...
I don't have any idea how he did it, but Pope Leo...

The Sermon on the Mount, Part I: Matthew...
The Sermon on the Mount, Part I (Matthew 4:12-5:12) St. Matthew moves...
view all Family, Parenting and Religion blogs
Ad-Free & Subscriber Log-In Subscription Support
- About Us
- 2026 Calendar
- Videos
- Podcasts
- Library of World Religions
- Faith In Media Tracker
- Advertise With Us
- Write for Us
- Privacy Policy
- Terms of Service
- Do Not Sell My Data
- Contact Us
- Radiant Digital
- Manage Newsletter Subscriptions
- Unsubscribe From Notifications
- Sitemap
Copyright 2008-2026, Patheos. All rights reserved.
Subscription Support Ad-Free & Subscriber Log-In
Follow Patheos